


Copyright Notice
Attribution Statement: LactMed is a registered trademark of the U.S. Department of Health and Human Services.
Bookshelf ID: NBK534420PMID: 30489718

An official website of the United States government

NCBI Bookshelf. A service of the National Library of Medicine, National Institutes of Health.
Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development; 2006-.
CASRN: 1969264-35-4
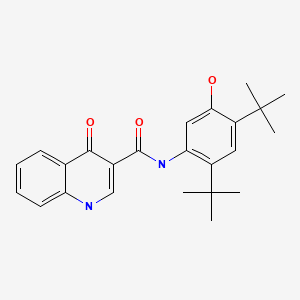
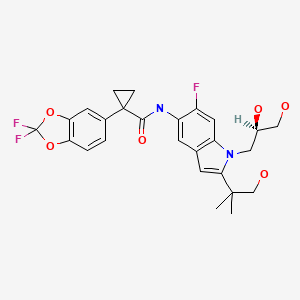
An international survey of cystic fibrosis centers found no adverse effects in breastfed infants of mothers taking these drugs. A task force respiratory experts from Europe, Australia and New Zealand found that these drugs are probably safe during breastfeeding.[1] Infants exposed to CFTR modulators through breastmilk should have periodic liver function testing and an examination by an ophthalmologist for cataracts. Because CFTR modulators can mask cystic fibrosis in breastfed infants, testing of breastfed infants for CF should be performed. Detailed monitoring recommendations have been published.[2]
Maternal Levels. Information on the concentrations of ivacaftor and tezacaftor in maternal milk can be found in the record on Elexacaftor, Tezacaftor, and Ivacaftor.
Infant Levels. Information on the concentrations of ivacaftor and tezacaftor in infant serum can be found in the record on Elexacaftor, Tezacaftor, and Ivacaftor.
A woman with cystic fibrosis was treated with lumacaftor and ivacaftor during pregnancy and postpartum. Her infant was fully breastfed until day 29 postpartum when elevated direct and indirect bilirubin, aspartate aminotransferase (AST), and alkaline phosphatase were found to be elevated. All values had been normal on days 1 and 14. The proportion of breastmilk the infant received was reduced to 25% and all values were normal on day 37. The fraction of breastfeeding was increased to 50% and then to 100%. On day 135, the infant's direct bilirubin was elevated during concurrent maternal levofloxacin and trimethoprim-sulfamethoxazole therapy. The fraction of breastfeeding was decreased to 75% and the direct bilirubin was normal on day 154. The authors noted that the abnormal test results could not definitively be attributed to lumacaftor and ivacaftor therapy.[3]
A survey was sent to lead clinicians of adult CF centers in Europe, the United Kingdom, United States of America, Australia and Israel requesting anonymized data on pregnancy outcomes in women using CFTR modulators during pregnancy and lactation. Responses were received from 31 centers and one woman with CF for a total of 64 pregnancies in 61 women resulting in 60 live births. Thirteen infants were breastfed on ivacaftor alone, 9 infants were breastfed on lumacaftor and ivacaftor, and 5 infants were breastfed on tezacaftor and ivacaftor for a total of 27 infants exposed to ivacaftor in breastmilk, all with no reported complications. The extent of breastfeeding was not reported.[4] An updated survey by the same authors asked CF clinicians to report on pregnant women exposed to the elexacaftor, tezacaftor and ivacaftor combination during pregnancy and breastfeeding. Twenty-six infants were breastfed (extent not stated) during maternal use of the combination. No adverse effects were reported in the breastfed infants.[5]
An infant was born to a mother taking elexacaftor, ivacaftor and tezacaftor for cystic fibrosis. The infant was breastfed (extent not stated). Although the infant had cystic fibrosis-causing CFTR mutations, the infant was healthy and tested negative for cystic fibrosis on newborn screening. The authors expressed concern that the drugs received transplacentally and in breastmilk caused a false negative screening test.[6]
A mother who was a heterozygous carrier of the F508del gene became pregnant with a homozygous infant. At 32 weeks of pregnancy, the mother began elexacaftor, ivacaftor and tezacaftor in the usual adult dosage to treat her fetus who had evidence of meconium ileus. The infant was born at 36 weeks and given pancreatic enzyme replacement therapy with breastfeeding while maternal treatment continued. The infant’s fecal elastase, transaminases and bilirubin were normal at about 1 month of age. The infant’s sweat chloride, although low, was nearer to normal than was expected. The authors hypothesized that the medications received in breastmilk moderated the disease process in the infant.[7]
Three women with cystic fibrosis were taking elexacaftor, ivacaftor and tezacaftor in unspecified dosages during pregnancy and postpartum while breastfeeding. On routine visual examinations between 8 days and 6 months postpartum, their infants were found to have small ( < 1.0 mm) bilateral cataracts, in the central area in one and outside the visual axis in the other two. Breastfeeding was discontinued after diagnosis at 16 days, 9 weeks and 6 months postpartum. The contribution of breastfeeding to the cataracts could not be determined.[8]
Two women were reported by the British Columbia cystic fibrosis clinic who became pregnant and breastfed their infants. One took ivacaftor and breastfed (extent not stated) for 42 months. Her infant was physically normal and healthy, but had speech delay. The other woman took Tricafta (ivacaftor, elexacaftor, and tezacaftor). She breastfed (extent not stated) her infant for 6 months and her infant had no complications.[9]
A woman with cystic fibrosis took ivacaftor 150 mg, tezacaftor 100 mg and elexacaftor 200 mg in the morning and ivacaftor 150 mg at night during pregnancy and breastfeeding (extent not stated). The infant had not regained his birthweight at 10 days postpartum, his stools had a greasy rim, and he had pancreatic elastase levels below levels for pancreatic sufficiency but higher than expected for newborns homozygous for this mutation. The infant was started on pancreatic enzymes and by day 20, he had normal elastase levels. By day 45 of life was gaining weight and stools were normal. At 6 months of age the infant was still being breastfed and doing well. The authors felt that when breastfeeding is stopped, a rebound in symptoms might occur because the infant will no longer be receiving small amounts of the mother’s medications through milk.[10]
A woman with cystic fibrosis received elexacaftor 100 mg, tezacaftor, 50 mg, ivacaftor 75 mg and additional ivacaftor 150 mg daily from 12 weeks of pregnancy and postpartum. The mother exclusively breastfed her infant while continuing therapy, and no significant side effects related were observed in the infant up to at least 3 months of age.[11]
Relevant published information was not found as of the revision date.
Tezacaftor and Ivacaftor
873054-44-5 1152311-62-0
Breast Feeding
Milk, Human
Chloride Channel Agonists
Cystic Fibrosis Transmembrane Conductance Regulator Protein Modulator
CFTR Protein Modulator
Disclaimer: Information presented in this database is not meant as a substitute for professional judgment. You should consult your healthcare provider for breastfeeding advice related to your particular situation. The U.S. government does not warrant or assume any liability or responsibility for the accuracy or completeness of the information on this Site.
Attribution Statement: LactMed is a registered trademark of the U.S. Department of Health and Human Services.
Your browsing activity is empty.
Activity recording is turned off.
See more...